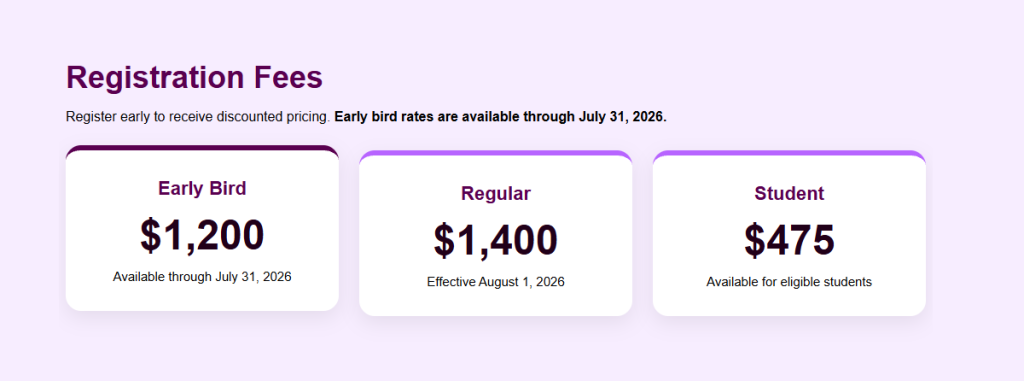
Interested in AI and Public Health? This Post Could Save You $1,400
Artificial intelligence is coming to public health.
Actually, based on the program for the first annual Artificial Intelligence and Public Health Conference (AIxPH), it is already here.
The National Network of Public Health Institutes is bringing together public health practitioners, technologists, researchers, policymakers, community organizations, and others in Baltimore from October 14–16, 2026. The program covers everything from AI governance and prompt engineering to disease surveillance, community health assessments, data modernization, health communication, privacy, environmental health, and workforce development.
There is just one problem.
Attending a national conference can be expensive. Once registration, airfare, hotel rooms, meals, and several days away from work are included, the real cost can climb well beyond the registration fee. That is especially difficult for local health departments and community organizations already being asked to accomplish more with limited staff and resources.
So we did something simpler. We read the AIxPH program.
More specifically, we reviewed the session descriptions and abstracts in the conference agenda and looked for recurring ideas. This is not a substitute for attending the conference. You will not get the workshops, conversations, networking, demonstrations, or opportunity to ask presenters questions.
But if you want to know where AI in public health appears to be heading, the program provides a surprisingly good snapshot.
And several themes come through very clearly.
1. Public Health Has Moved Beyond Asking Whether It Should Use AI
Perhaps the most important thing about the AIxPH program is what is largely missing. Relatively few sessions are devoted simply to explaining what artificial intelligence is.
Instead, the conference opens with examples of AI already being explored or implemented in governmental public health. Those examples include surveillance, survey analysis, communications, analytics, and decision support. Presentations describe possibilities such as accelerating BRFSS data analysis, improving small-area estimation, connecting authoritative public health information to AI systems, and using AI-supported approaches to reach audiences through trusted digital creators.
That represents an important maturation of the conversation.
The question is increasingly becoming: How do we use AI well?
That shift appears throughout the program. Public health organizations are experimenting with AI for community health assessments, program evaluation, health communication, data exchange, patient education, grant writing, surveillance, GIS, workforce training, and administrative work.
The conference therefore suggests that 2026 may represent an important transition point: AI is moving from novelty to infrastructure. And infrastructure creates a different set of problems.
2. Governance May Be More Important Than the Technology
If one theme runs through almost the entire conference, it is governance. One workshop walks organizations through developing an AI policy, including purpose, scope, privacy, transparency, human oversight, bias mitigation, training, procurement, accountability, and monitoring. Elsewhere, sessions tackle enterprise governance, validation, assurance, data governance, legal compliance, human oversight, equitable governance, and even the process for retiring AI systems that organizations should no longer use.
This tells us something important about where the field is going. Buying a ChatGPT license is not an AI strategy. Neither is telling employees to “experiment with AI.” Organizations eventually need to answer much harder questions:
Who can use AI? What information can employees put into it? Which decisions can AI support? Which decisions require human review? How are outputs validated? How are vendors evaluated? Who is accountable when something goes wrong? How are communities involved? And what happens when a model becomes outdated?
These are organizational questions, not technical ones. One particularly interesting session goes even further and addresses AI decommissioning. Its premise is that public health has begun thinking about how to introduce algorithms but has few established practices for deciding when to turn them off. Participants are asked to inventory systems, make a retirement decision, document what a retired model did, and develop a process for communicating with affected communities.
That signals a field beginning to think about the entire AI lifecycle rather than simply adoption.
3. The Biggest Barrier May Not Be Technical Skill
Another striking theme is workforce readiness. One session summarizes the challenge particularly well: public health agencies are being asked to integrate AI while simultaneously dealing with limited staffing, limited funding, expanding responsibilities, and little time for training. Its proposed solution is not sophisticated machine learning training. It is starting with simple activities such as improving emails, summarizing documents, organizing information, and planning work.
That idea appears repeatedly across the agenda.
Sessions address AI literacy, adult learning, workforce development, human-AI collaboration, community health worker training, and experiential AI education. One 10-week applied capstone program, for example, has students use AI and data science on real public health problems affecting rural and underserved communities.
This suggests that AI literacy is not the same thing as AI expertise.
Most public health workers probably don’t need to understand transformer architecture or train neural networks (though it doesn’t hurt!). They do need to understand what these systems can do, what they cannot reliably do, what information is appropriate to provide them, how to evaluate an output, when human judgment is necessary, and how to recognize potential bias or failure.
The conference agenda even contains a session titled “Literacy Before Skill.” That may be one of the most useful principles public health organizations can take away from the entire meeting.
4. Start With Boring AI
There is another practical lesson buried in the abstracts. Many of the most realistic applications of AI are not futuristic. They are mundane.
The prompt-engineering workshop identifies tasks including grant writing, drafting communications, summarizing information, creating meeting materials, conducting environmental scans, and supporting analysis and decision-making. Another workshop explicitly encourages organizations to start with low-risk activities that require little funding or technical expertise.
This matters because organizations can easily approach AI backward. They start by asking: What can we do with AI?
A better question is: What repetitive, expensive, slow, or frustrating part of our work are we trying to improve?
Only then should AI enter the conversation. For many health departments, the first transformative AI application may not involve predicting an outbreak.
- It might involve turning 300 pages of community feedback into an initial qualitative synthesis (and yes, we here could help you with that)
- It might be producing the first draft of a community health assessment section.
- It might be transforming technical surveillance findings into plain-language communication.
- It might be finding relevant information buried across organizational documents.
That is considerably less glamorous than “AI-powered public health.” It may also be considerably more useful.
5. Public Health Data Infrastructure Still Matters
The conference also contains an implicit warning against believing that AI can compensate for poor data systems. One lightning talk says it directly: “Data is the foundation, AI is the acceleration.”
Several other sessions reinforce the same point. A GIS demonstration emphasizes combining authoritative health, environmental, and community data with AI capabilities. Another workshop demonstrates a public-health-specific AI tool drawing on sources such as the American Community Survey, CDC WONDER, and CDC PLACES. I like that in theory, but getting down and dirty with the data has its own conceptual advantages.
And a Medicaid implementation describes something far more complicated than simply connecting an organization to a language model: secure APIs, controlled data pipelines, legacy-system integration, approval processes, stakeholder validation, documentation, human benchmarks, and PHI protections.
The lesson is straightforward. AI does not make interoperability, data quality, metadata, provenance, or governance disappear. If anything, AI makes those things more important because it allows organizations to act on information faster and at greater scale. Bad infrastructure plus faster automation can simply produce bad decisions faster.
6. Public Health Is Beginning to Move From Chatbots to AI Systems
Another subtle trend is the movement beyond standalone chatbots.One opening presentation discusses APIs, Model Context Protocol servers, provenance-linked data, and ways of helping AI systems reliably locate and cite authoritative public health evidence.
Elsewhere, the program includes agentic AI policy gates, AI-assisted data exchange, governed AI pipelines, AI-supported repository curation, local language models, and AI integrated into existing operational workflows.
The first wave of generative AI adoption largely involved humans sitting in front of a chatbot. The next wave is likely to involve AI embedded inside systems and workflows.
Instead of: Human → chatbot → answer
we increasingly get something closer to: Data → AI → organizational rules → human review → action
That is potentially much more useful. It is also much harder to govern.
At this point, can I interest you in trying our literature-search personalization agent?
Build Your Public Health Issue
Tell us a little about your work, and we’ll build a personalized issue with five things worth knowing.
7. “Human in the Loop” Is Becoming a Design Requirement
Across the abstracts, AI is repeatedly framed as something that should augment, not replace, professional judgment.
The public health communication workshop explicitly says generative AI should support campaigns without replacing human expertise, critical thinking, audience knowledge, or community input.
The local health department workshop makes essentially the same point: AI can assist with dashboards, maps, reports, grant writing, and decision-making, but it should not replace public health expertise or professional judgment. Even the conference roundtables include a session explicitly titled “Augmenting, Not Automating.”
This may become a central implementation principle for public health AI. The goal is not necessarily to remove humans from public health work. It is to determine which parts of a task machines can accelerate and which parts require human judgment, relationships, contextual knowledge, or accountability.
8. Equity Cannot Be Added After Deployment
Equity appears throughout the program, but some sessions push the conversation beyond generic statements about “responsible AI.” The Tribal and Indigenous health session is especially important. It identifies problems with representation in training data, Tribal data sovereignty, fragmented government-to-government data infrastructure, and the absence of adequate governance for AI systems accessing Indigenous data.
AI systems learn from existing data. Public health data come from existing social systems. Those systems contain gaps. Some populations are measured poorly. Some are systematically missing. Some variables proxy structural inequities. Some communities have legitimate claims over how their data are collected and used. An AI system can therefore reproduce inequity without anyone deliberately programming discrimination into it (which people have been talking about for YEARS)
One conference workshop describes an equity framework spanning the entire AI lifecycle, from problem definition and data collection through deployment, monitoring, and correction. That lifecycle perspective is important. You cannot build an inequitable system and “check for bias” at the end.
9. AI Creates New Public Health Problems, Not Just New Public Health Tools
One of the most interesting aspects of the conference is that it does not treat AI exclusively as something public health organizations use. AI itself can become a public health exposure.
A session on information environments explores AI-generated low-quality health information and misinformation as potential threats to health. Community health workers are testing screening approaches that examine social media exposure, chatbot responses, receptivity to misinformation, and other characteristics of people’s information environments. Another session addresses the environmental consequences of data centers, including their potential effects on communities already experiencing environmental injustice. The lightning talks also include work on environmental harms associated with AI, misinformation detection, community governance, and what AI hallucinations and refusals may reveal about gaps in public health knowledge.
Public health has at least two jobs here: use AI responsibly and study and respond to the health consequences of society’s use of AI. Those are different responsibilities.
10. Privacy Is Getting Much More Complicated
Traditional health-data privacy frameworks were not designed around general-purpose generative AI. The conference includes sessions on HIPAA-compliant architectures, local language models, data sovereignty, and the limits of existing privacy protections.
One workshop demonstrates running a language model entirely on a laptop with Wi-Fi turned off so that information does not have to be transmitted to a cloud service (probably Ollama, which is pretty simple to do).
Another session argues that health information can fall outside expected HIPAA protections depending on who holds it, how identifiers are handled, and how AI systems process or infer information. It highlights particularly sensitive contexts such as reproductive health, behavioral health, substance use, immigration status, and infectious disease.
The practical implication is that “Is this HIPAA compliant?” is no longer a sufficient privacy strategy.
Organizations need to understand where data go, who retains them, how models use them, what new information can be inferred, and what happens to information after a user submits a prompt.
11. Vendor Selection Is Becoming a Public Health Competency
AI adoption has also created a new challenge for public health leaders: Everyone wants to sell you AI.
The AIxPH vendor-selection workshop proposes evaluating tools based on organizational readiness, build-versus-buy decisions, interoperability, security, knowledge transfer, and cost structure. It also warns organizations to distinguish quoted prices from actual implementation costs and to involve IT, legal, and finance stakeholders early.
That last point deserves considerably more attention across public health. Software cost is not implementation cost.
Organizations also need staff time, workflow redesign, training, integration, security review, governance, evaluation, maintenance, and eventually perhaps migration or decommissioning.
The question should be: “What will it cost us to produce a measurable improvement in this public health function?”
That is a much harder question for a vendor to answer. It is also the question public health should be asking.
12. Public Health AI Is Becoming Local
Some of the most promising material in the agenda is not about enormous national AI systems. It is about highly specific applications.
The program includes AI-assisted community health assessments, evaluation tasks, community health worker dashboards, cancer survivorship outreach, quitlines, no-show prediction, legal epidemiology, autopsy and toxicology data, rural recovery support, immunization systems, women’s health engagement, qualitative analysis, public health campaigns, and local GIS applications.
That may be where the greatest near-term opportunity lies. Public health does not necessarily need one enormous “public health AI.” It may need hundreds of small, carefully governed applications that each make one part of public health practice faster, easier, more equitable, or more effective.
So, What Should a Health Department Actually Do?
After reading the conference program, our synthesis is surprisingly practical.
Don’t start by buying AI. Start by identifying work.
Find something that consumes staff time, has a reasonably clear output, carries manageable risk, and can still be reviewed by a knowledgeable person. Communications, summarization, meeting preparation, evidence scanning, document classification, and administrative workflows may be better starting points than automated decisions affecting individuals.
Then establish basic rules for data, privacy, human oversight, and validation.
Build staff literacy. Measure whether the tool actually improves anything. And only then expand.
The conference itself offers evidence that adoption is still uneven. A session drawing on ASTHO data reports that 64% of state and territorial agencies have an AI policy, while only 14% use AI for disease surveillance; 64% cite a lack of established guidance as their top barrier.
In other words, public health does not appear to have an AI technology shortage. It has an implementation problem.
The Bigger Picture: AI Is an Implementation Science Problem
AI adoption in public health looks remarkably similar to the adoption of almost every other innovation. An innovation can be technically impressive and still fail.
It has to fit existing workflows. People have to understand it. Leadership has to support it. Organizations need sufficient resources and infrastructure. Users need confidence in it. Policies need to accommodate it. Communities need reasons to trust it. And someone has to determine whether it is actually producing better outcomes.
The AI in Public Health ECHO session captures this problem directly: one-time pilots rarely become sustainable programs without investment in workforce capacity, organizational infrastructure, leadership support, and public trust.
That is not fundamentally a machine-learning problem. It is an implementation problem. And public health already knows quite a bit about implementation.
What AIxPH 2026 Tells Us About the Next Phase of Public Health
Reading across the AIxPH abstracts, the field seems to be entering a second phase of AI adoption.
The first phase was experimentation: “Look what ChatGPT can do.”
The next phase is institutionalization: “How do we make this useful, safe, sustainable, equitable, measurable, and accountable?”
That requires less fascination with individual tools and considerably more attention to workflows, governance, data infrastructure, workforce capacity, interoperability, privacy, evaluation, community engagement, and implementation.
Those are areas public health understands.
Public health does not need to become Silicon Valley. It needs to take the things the field already knows about evidence, systems, equity, community, implementation, and population health and apply them to a new class of technology.
AI will change. The tools discussed at the 2026 conference will probably look primitive five years from now.
But the questions underneath them will remain:
- Does this improve public health?
- For whom?
- At what cost?
- Compared with what?
- Who bears the risk?
- Who gets a voice in the decision?
- And how will we know whether it worked?
Those are not AI questions. Those are public health questions.
We Just Saved You $1,400. Let Trawly Keep Going.
If you found this useful, this is exactly what Trawly is built to do. Far more public health research, guidance, and emerging technology exists than any one person has time to track. Trawly watches the evidence for you, identifies what matters, and turns it into practical intelligence you can actually use.
You just got the major lessons from an expensive conference without having to attend. Imagine doing the same thing with the hundreds of new public health studies published every week.
Subscribe to Trawly and spend less time searching for evidence and more time using it.